Rural Health Clinics

Always-On Advanced Primary Care

Rural health clinics can now receive CMS reimbursement for a standing relationship with a patient rather than for minutes on a timesheet. Praventa supplies the connectivity, the clinical team and the round-the-clock access that keeps that relationship running, without adding payroll or any out of pocket costs.

The Model

Why do rural health clinics leave care management revenue uncaptured?

As a Rural Health Clinic, your mission is to provide an essential safety net for your community. However, severe staffing shortages, heavy administrative burdens, and strict compliance windows often make it impossible to capture critical care management revenue.

A small single-story rural clinic building set against open foothills and farmland.

Praventa Health acts as a seamless clinical extension of your team. We manage the non-face-to-face requirements of all advanced primary care functions including transitional care, medication management, and chronic care management.

The 30 days following discharge are among the most vulnerable for a patient, but transitional care should rarely be where the work ends. The same patient who was just discharged typically has two or more chronic conditions, making that 30-day window a natural on-ramp into Chronic Care Management where someone remains present between visits rather than waiting for the next acute event.

Medication is where those two programs meet: a regimen changed during an inpatient stay is the single most common reason a rural patient deteriorates after going home, which is why Comprehensive Medication Management runs alongside both, with a pharmacist assessing every medication a patient is actually taking rather than the list in any one chart.

What has changed is how that work can be paid for. Advanced primary care management, reported with G0556, G0557 and G0558, is a monthly bundled payment per patient, stratified by complexity rather than by effort, and it carries no monthly time threshold at all.

The reporting question stops being how many minutes were documented and becomes whether the required service elements were in place for that patient that month. For a clinic whose binding constraint is staff hours, that is the most consequential difference in the entire code set. It is a replacement rather than an addition. The bundle incorporates elements of transitional, chronic and principal care management, so those are not separately reported for the same patient in the same period.

Whether the bundle is favorable depends on your panel rather than on the code descriptors, and that is an analysis of your own data. Praventa runs it with you before anything moves.

For a rural clinic, the constraint on all three is the same, and it is not clinical. It is having enough hands to do the non-face-to-face work on time, every month, for every eligible patient. Outsourcing that layer to Praventa extends your access to care without extending your payroll: the panel gets continuous coverage, the encounters come back to your clinic, and your providers keep doing the work only they can do.


Always On

What always-on actually means

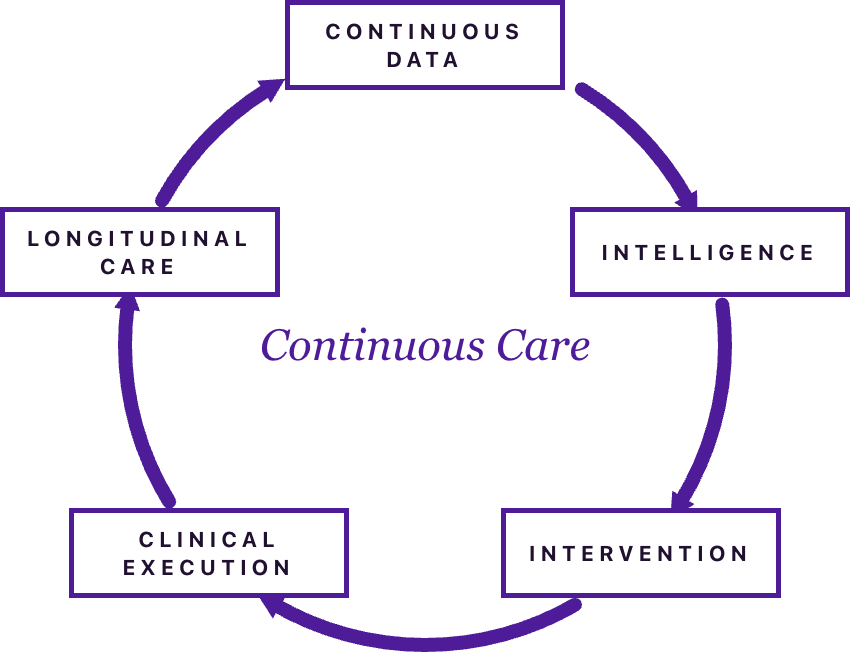
A monthly bundle pays for a relationship that does not switch off between visits. That is only deliverable if the information never stops arriving and somebody is always there to act on it.

A loop diagram: continuous data leads to intelligence, intelligence to intervention, intervention to clinical execution, clinical execution to longitudinal care, and longitudinal care back to continuous data, with continuous care at the center.

Praventa connects once, through the Trusted Exchange Framework and Common Agreement and its designated Qualified Health Information Networks, and through statewide and regional data exchange frameworks. Two kinds of information come back.

Event notifications tell us the moment one of your patients is admitted, transferred or discharged, anywhere that reports. Longitudinal records tell us what has happened to that patient across every facility that contributes, not only what is written in your chart.

Event data alone makes a program reactive: something happens, somebody responds.

The longitudinal record is what makes the relationship continuous, because the picture of the patient keeps filling in whether or not they have been seen recently. That is the difference between a vendor that counts minutes and a clinical layer that is genuinely always on.

Access runs the same way. Advanced primary care management requires round-the-clock access to the care team, and Praventa provides it above and beyond what your own providers staff. A patient who deteriorates at nine on a Saturday evening reaches a clinician rather than a voicemail greeting, and what happens in that call comes back to your clinic as part of the record.

What We Supply

What Praventa supplies against the service elements

Because the bundle pays on elements being in place rather than on minutes documented, the only question that matters is what is actually covered, and by whom. Here are all thirteen service elements, and which of us supplies each one.

Service element
What it requires
Responsibility
01Patient consent
Captured once at enrollment and documented.
Praventa
02Initiating visit
Only for new patients, and only the billing practitioner can do it.
Your clinic
0324/7 access to care
A clinician reachable at any hour, beyond what you staff.
Praventa
04Continuity of care
A named pharmacist or nurse practitioner who stays with the patient.
Praventa
05Comprehensive care management
Needs assessment, preventive review and medication reconciliation.
Praventa
06An electronic care plan
Built and maintained, shared with your team and the patient.
Praventa
07Management of care transitions
Discharge alerts, outreach in two business days, follow-up to you.
Praventa
08Coordination with community-based services
Referral to home and social services, documented in the care plan.
Shared
09Ongoing patient communication
A reliable route to the care team during business hours.
Praventa
10Enhanced communication
Secure messaging and asynchronous channels beyond the telephone.
Praventa
11Population-level data analysis
Care gaps and medication risk surfaced across the whole panel.
Praventa
12Risk stratification
The panel ranked so deterioration is visible before it happens.
Praventa
13Performance measurement
Outcome reporting from us; MIPS or MVP reporting stays with you.
Shared

If you are an independent physician practice rather than a certified Rural Health Clinic, the billing mechanics differ and that version of this page is the one to read.

Praventa also runs eligibility and tier identification, including the monthly dual-eligible and qualified Medicare beneficiary screening that determines which of the three codes applies. That is billing-level work rather than a service element, which is why it sits outside the thirteen.

The Praventa Advantage

No upfront costs. No tech fees. No internal burnout. Real turnkey care management.

We eliminate the traditional barriers that stop rural health clinics from launching care management programs.

An older couple seated in a bright rural clinic lobby smiling in conversation with a physician, with farmland visible through the window.
01

Zero fees

There is no out-of-pocket cost to stand up your care management programs, and none to interconnect with the networks that make transitional care work. Praventa carries the connection through the Trusted Exchange Framework and Common Agreement (TEFCA), its designated Qualified Health Information Networks, and state or regional exchanges, so we ingest real-time hospital discharge notifications and route them into our workflows on your behalf. No integration invoice, no subscription, no predatory vendor fee to hook into an exchange.

02

Turnkey clinical workforce

Our remote team of clinical professionals handles the tedious, time-consuming telephone tracking, intensive patient coaching, and medication reconciliations.

03

Seamless chart integration

Praventa does not operate as a data silo. We deliver fully formatted, compliant encounter summaries directly to your team to upload as clean PDFs into your primary EHR, supporting audit defense.

04

Unclaimed revenue

Most rural clinics are already eligible for far more than they bill. Transitional Care Management pays per discharge and goes uncaptured on the majority of eligible discharges nationally. Chronic Care Management pays every month a qualifying patient is managed, and most eligible panels are never enrolled at all. Comprehensive Medication Management adds pharmacist-led review on top of both. Praventa does the work that makes all three billable, and the completed encounters come back to your clinic.

Grant Support

Ready-made grant packages: funding your internal transition

Even with Praventa handling the clinical outreach, updating your clinic's workflows requires internal staff time and resources. You should not have to pay out of pocket to modernize your care models.

A rural Oregon valley in morning light, green pasture and a fence line with conifer forest and mountains beyond.

Praventa provides rural health clinic executives with ready-made grant application packages built for the State Rural Health Transformation Program, which CMS is distributing to all fifty states, along with your state Medicaid agency's infrastructure funds and your regional managed care plan's capacity grants. When you partner with us, we hand you pre-written proposal text targeting awards of $50,000 to $100,000 to support the work of implementing care management, across three critical operational areas.

01

Workforce capacity extension

Grant funding offsets the hourly wages of dedicating an internal medical assistant or clinic liaison. This person serves as our secure on-site bridge, uploading Praventa's care summaries and routing high-risk clinical alerts directly to your on-site providers.

02

Clinic access optimization

Meeting Medicare's 7 or 14 day post-discharge visit timeline requires immediate appointments. Grant dollars fund the restructuring of your scheduling templates, absorbing the operational cost of reserving rapid-access slots for TCM patients.

03

Social needs and patient transport

Geography is the barrier that defeats rural programs most often. Our grant packages help you establish a dedicated patient transit pool, including rideshare vouchers, gas cards and non-emergency medical transport, so distance never causes a patient to miss their billable face-to-face follow-up encounter.

State Associations

What a statewide, always-on advanced primary care network is worth

Praventa Health, Inc. partners with state rural health associations and regional primary care associations to build something no single clinic can build alone: one always-on network covering the rural communities across an entire state, with transitional care as the front door and advanced primary care management as the relationship that follows.

An agricultural valley at dusk, orchard rows running toward low foothills under a violet sky.
01

One standard of care, every community

Instead of each member clinic improvising its own post-discharge follow-up, every rural community in the state gets the same two business day contact, the same medication reconciliation and the same documentation standard, whether the clinic has two providers or twenty. That consistency is what makes a state-level measure move.

02

Interoperability without a project per clinic

Connecting one small clinic to a health information network is a project it cannot staff. Praventa connects once, through TEFCA designated Qualified Health Information Networks and the state or regional exchange, then extends that pipeline to every member clinic without exhausting the association's technical assistance budget.

03

A shovel-ready model for state funding

The State Rural Health Transformation Program is distributing funds to all fifty states, and associations are being asked what to build with them. A network already running across member clinics is a concrete proposal rather than a plan, and it shows funding landing in active, measurable rural care coordination.

04

Reimbursement that stays in the community

When member clinics do not bill for transitional or chronic care management, that federal reimbursement never reaches the rural economy at all. A statewide network recovers it clinic by clinic, and the collective reduction in 30-day readmissions shows up in the state's own rural health measures.

05

A model the smallest member can sustain

A monthly bundle that pays on service elements rather than on documented minutes removes the reason small clinics quietly stop billing. The two-provider clinic runs the same program as the twenty-provider clinic, so the weakest-staffed member is no longer the ceiling on what the network can promise.

06

Performance you can actually compare

When every member runs the same service elements and documents them the same way, the association can see performance across the network instead of clinic by clinic. Without that, the honest answer to how rural care management is going statewide is that it varies by clinic, and no one can say by how much.

Common Questions

Related questions

Can a Rural Health Clinic bill transitional care management and chronic care management for the same patient in the same period?

Yes, and this is where rural health clinics differ from most practices. For a physician practice, CMS and CPT specify that the two are generally not billed in the same calendar month. RHCs and FQHCs are treated differently and may bill both for the same patient during the same period, provided every billing requirement is met and the dates of service do not overlap. Most vendor guidance repeats the practice rule and gets this wrong for rural clinics. One caveat: this applies while the patient is being managed under those codes. If the same patient moves onto advanced primary care management, that bundle incorporates both, and they are no longer separately reported for that period.

Is there a time requirement for advanced primary care management?

No, and this is the clearest break from every other care management code. The monthly payment is stratified by patient complexity rather than by documented minutes, so the reporting question is whether the required service elements were in place, not how long they took. For a rural clinic that cannot reliably capture and document a minute threshold every month for every eligible patient, this is the difference between a program that works and one that quietly stops being billed.

What changes when a patient moves to advanced primary care management?

The bundle replaces rather than adds. Advanced primary care management incorporates elements of transitional, chronic and principal care management, so those are not separately reported for the same patient in the same period. Whether that is favorable depends on the panel rather than on the code descriptors: a panel where documented time reliably clears the thresholds behaves differently under a bundle than one where it does not. That is an analysis of your own data, and Praventa runs it with you before any patient is moved.

How do rural health clinics bill care management now that G0511 is gone?

HCPCS G0511 was the single general care management code for RHCs and FQHCs, and it is terminated. Since January 2025 rural clinics report the individual CPT and HCPCS base and add-on codes for each care coordination service instead, and from January 2026 those designated care management services are paid at the national non-facility rate. The codes in force are published annually with the Physician Fee Schedule final rule addenda, so confirm the current table rather than working from an older reference.

Does the clinic need to hire staff to run a care management program?

No. The work that consumes staff time is the non-face-to-face work: identifying the discharge, reaching the patient inside the required window, reconciling medications and documenting all of it. Praventa performs that remotely. Clinical staff may furnish those elements under the billing practitioner's general supervision, which is what makes the model work without adding payroll.

Who conducts the required face-to-face visit?

Praventa clinical professionals do. Our nurse practitioners conduct the required face-to-face visit by telehealth, in coordination with your providers, inside the seven or fourteen day window that applies to the patient's complexity. Your clinic is not asked to fit that visit into its own schedule, which is usually the constraint that stops a rural program from meeting the timeline at all. The visit, the medication reconciliation and the supporting documentation come back to your team as part of the episode record.

How does hospital discharge information reach a rural clinic in time to act?

Through the exchange layer rather than the fax machine. Praventa connects to the Trusted Exchange Framework and Common Agreement and its designated Qualified Health Information Networks, and to state and regional health information exchanges, then routes real-time admission and discharge notifications into the workflow. The two business day contact requirement is the reason this matters: a discharge you learn about on day four is a discharge you cannot bill.

What does it cost a clinic to start?

There is no upfront cost and no integration fee. Praventa carries the cost of connecting to the exchange networks and supplies the remote clinical workforce. For the internal work that remains, such as dedicating a liaison and restructuring scheduling templates to hold rapid-access slots, we provide ready-made grant application packages written for the State Rural Health Transformation Program and comparable state and managed care funding.

How does transitional care management lead into chronic care management and medication management?

A discharge is a fixed event with a fixed window, which makes transitional care the natural place to start. The same patient usually carries two or more chronic conditions, so the thirty-day period is the on-ramp into chronic care management, where someone stays present between visits. Medication is where both meet: a regimen changed during an inpatient stay is among the most common reasons a rural patient deteriorates at home, which is why comprehensive medication management runs alongside both with a pharmacist assessing what the patient is actually taking.

Talk to us about your clinic or your member network

Praventa operates care management programs with its own clinical team and licenses the same platform to organizations running them in-house. Tell us how your clinic or association is structured and we will tell you which model fits.

Contact Praventa